A six-week trial found short-term symptom improvement with caffeine, but a longer study found no lasting benefit over placebo.

A short course of caffeine improved Parkinson’s symptoms in one small clinical trial, but a longer study did not find that benefit. The difference matters: an early change over weeks doesn’t establish caffeine as a lasting treatment, and the available evidence doesn’t support using it as symptom therapy.
What the trials found
In a six-week, randomized, double-blind, placebo-controlled study, researchers tested caffeine in people with Parkinson’s disease. Participants began with an amount roughly equivalent to one cup of coffee twice daily, then increased to about two cups’ worth twice daily. The article describes that later amount as comparable to four cups of black tea twice a day or six cups of green tea.
By the third week, the caffeine group had significantly better symptom scores than the placebo group. That result was encouraging, but the trial lasted only six weeks. It couldn’t show whether the improvement would continue, fade with regular use, or matter over a longer period. The study also tested caffeine in a particular research setting; it doesn’t establish that coffee itself, with its other compounds and variable caffeine content, has the same effect for every person.
Researchers later tested caffeine for more than six months. Participants with Parkinson’s were assigned to caffeine, at about two cups of coffee’s worth twice daily, or placebo. This longer study found no symptomatic benefit over placebo. Taken together, the trials suggest that a short-term change may not persist. They don’t show that caffeine slows the disease or prevents it from progressing.
The original article links to figures showing the trial results: 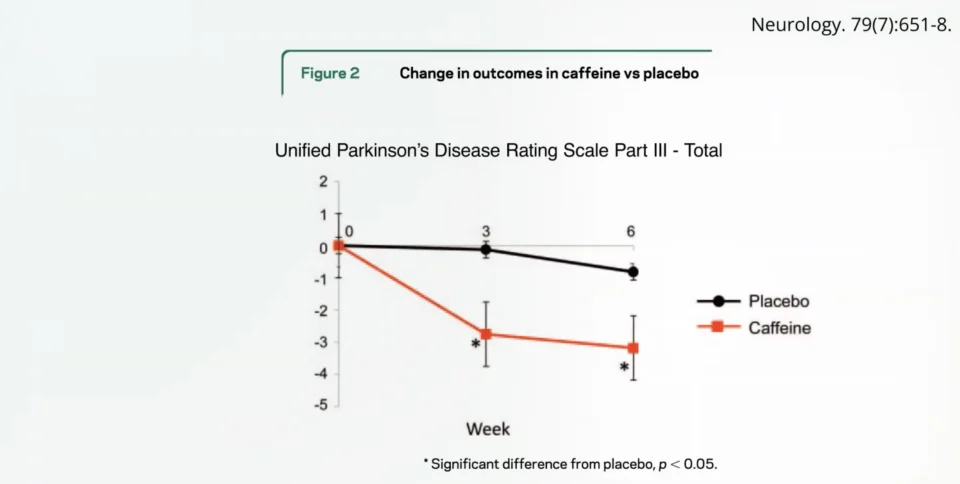 and
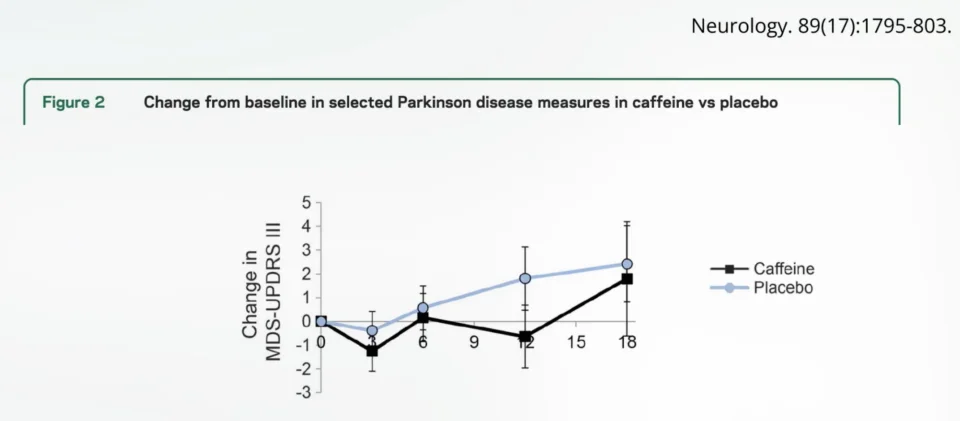 . Those figures reflect the separate study periods, so the six-week result should be read alongside the longer follow-up.
Why coffee drew interest
Interest in caffeine partly comes from observational research. Some population studies have linked coffee or caffeinated tea consumption with lower Parkinson’s risk, and one study cited in the source found that people with Parkinson’s who drank these beverages appeared to have a lower risk of premature death. Such findings can identify patterns, but they can’t establish that caffeine caused them. Differences in health, habits, or other factors may help explain an association.
That distinction is central when considering nutrition and Parkinson’s. Research has examined dietary patterns and individual foods for possible links with disease risk or symptoms, but findings about one food don’t establish that a particular diet treats the disease. The source discusses plant-based eating, antioxidants, and foods high in animal fat or protein as topics in observational and other research. These broad findings shouldn’t be turned into promises about prevention or treatment.
Nor does “plant-based” automatically mean safe or beneficial in every case. The source points to soursop, also called graviola, as an example of a plant food that has raised concerns because of potentially neurotoxic compounds. This is a reminder that food effects depend on the substance and evidence being studied; a general dietary label can’t settle the question.
What the evidence means for patients
The short trial’s improvement is worth understanding, but the longer placebo-controlled study carries an important practical message: the early result did not translate into a sustained symptom benefit. The authors cited in the source concluded that caffeine could not be recommended as symptom treatment for parkinsonism. The evidence presented here also doesn’t justify changing prescribed medication or relying on coffee to manage symptoms.
Caffeine can affect people differently, and coffee may be only one source in someone’s daily intake. Anyone considering a significant change in caffeine use, or wondering whether it could interact with their treatment or affect sleep and other symptoms, can raise the question with a doctor or pharmacist. They can consider the person’s health and medicines in context.
The next useful evidence would need to clarify whether any short-term symptom change can be reproduced and why it disappears in longer follow-up. For now, the careful reading is straightforward: caffeine showed an early signal in one six-week trial, but a study lasting more than six months found no benefit over placebo. That leaves coffee as a research question, not an established Parkinson’s treatment.
Related reading
The source also links to these pieces on Parkinson’s and diet:
- Preventing Parkinson’s Disease with Diet
- Treating Parkinson’s Disease with Diet
- Is Something in Tobacco Protective Against Parkinson’s Disease?
- Peppers and Parkinson’s: The Benefits of Smoking Without the Risks?
- Could Lactose Explain the Milk and Parkinson’s Disease Link?
- Parkinson’s Disease and the Uric Acid Sweet Spot
- The Role Meat May Play in Triggering Parkinson’s Disease
It also lists further reading on coffee: